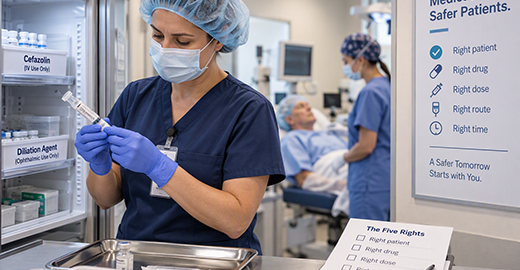
You have likely heard about the high-profile medication error cases that occurred at two Tennessee hospitals in recent history. This year, there were four related medication errors at Ascension St. Thomas Hospital resulting in serious harm to four patients. Prior to surgery, the patients were mistakenly given an epidural of potassium phosphate (often used to correct phosphorus levels in blood) instead of bupivacaine, a local anesthetic. After an investigation, the Tennessee Health Facilities Commission found in its report[1] that five syringes of incorrect medication for nerve blocks were prepared the day before surgeries. The error was not detected during the preparation, verification, and dispensation process despite the oversight of multiple hospital pharmacy personnel.
In 2017, a nurse administered the wrong medication to a patient resulting in a fatal error at Vanderbilt University Medical Center. The patient was scheduled to undergo a PET scan. She was anxious about the scan and was supposed to be given Versed. Instead, she was given a fatal amount of a paralytic, vecuronium. Subsequently, the nurse was criminally prosecuted for that error.
A 2024 study [2] found in the hospital setting that a medication error occurs approximately 6.5 times per 100 admissions.
Those medication errors occurred at large medical institutions that have protocols in place to deter medication errors. What about the many medical practices across the country, big and small?
A 2023 study published in the International Journal of Clinical Pharmacy[3], noted there is a “dearth of literature” in the outpatient setting.
The study found that medication errors in the outpatient setting are common.
In the May 2023 edition of SVMIC Sentinel, I wrote about another medication mix-up in Closed Claim: A Recipe for a Medical Emergency[4]. Unfortunately, Closed Claim is back with another medication error story.
Could this error have been avoided? Closed Claim asks you to be the judge.
Patient Jerry Gray was scheduled for cataract surgery. He was seventy-two years old with a complex medical history. He suffered from renal issues, had previously undergone hip replacement, was diabetic, and had been diagnosed with heart disease. Mr. Gray was a veteran of the U.S. Army and was loved by everyone but his three ex-wives. He was a well-known character in the community. DeDe Weiss was a registered nurse with several years of experience caring for patients. Their fates would intersect at a surgery center where Dr. Liza Harrison was scheduled to perform the cataract surgery.
On the morning of the surgery, Mr. Gray came with his adult son, as he would be unable to safely drive home after the procedure. Nurse Weiss was assigned to the surgery that would be performed by Dr. Harrison.
After obtaining Mr. Gray’s vitals, the plan was for Nurse Weiss to dilate his eye with a medication consisting of tropicamide, phenylephrine and cyclopentolate hydrochloride. This dilation agent was given to Mr. Gray as topical eye drops. As mentioned, Mr. Gray had a complex medical history. Because he previously had undergone a hip replacement, an antibiotic, Cefazolin was to be administered as well.
The surgery center stored medication that required cooling in a refrigerator. The Cefazolin and dilation agent were stored together in the refrigerator along with other medications. The dilation agent was pre-mixed and kept in 10cc syringes. The Cefazolin was also in 10cc syringes. Each syringe was correctly marked, indicating the medication that it contained.
The antibiotic was to be administered through an IV, the dilation agent was to only be given as eye drops. Nurse Weiss intending to get the antibiotic Cefazolin, reached in the refrigerator and grabbed a 10cc syringe--with the dilating agent in it. Without taking further precautions and with no further delay, she administered the entirety of the 10cc dilating agent through the IV to Mr. Gray. There were safety precautions that should have been taken which were not. We will discuss some of those later.
Almost immediately after receiving the medication, Mr. Gray made the comment that he felt “strange.” Nurse Weiss recounted later in her deposition that his comment seemed odd to her, as she had given patients the antibiotic, Cefzolin, many times before. Mr. Gray began to have trouble breathing and laid down on an examination table. He then began shaking uncontrollably.
Mr. Gray appeared to be having a seizure!
Nurse Weiss called for help. The surgery center code protocol was promptly activated. Another nurse responded along with Dr. Harrison. Mr. Gray’s vitals were trending negatively. A rebreather mask was placed and 911 was called. By the time EMS arrived, he was verbally unresponsive. Mr. Gray was transported to a nearby hospital emergency department. There, he was intubated.
On a day when the patient was scheduled to undergo a routine cataract surgery, he ended up in the ICU.
After the incident, Dr. Harrison asked Nurse Weiss to show her what she gave Mr. Gray. She obtained the syringe that had been discarded which was clearly marked “Dilation agent: tropicamide, phenylephrine and cyclopentolate hydrochloride.” This was clearly not a medication to be injected into a patient through an IV.
Given the extreme adverse reaction Mr. Gray experienced, in addition to his preexisting conditions, he spent five days in the ICU. Due to kidney issues and other past medical problems, there was great concern that Mr. Gray suffered permanent damage. He was lucky to be alive.
After some time had passed, Mr. Gray filed a lawsuit naming the surgery center for the negligent actions of DeDe Weiss, R.N. and for the negligent supervision, training, and hiring of Nurse Weiss. Dr. Liza Harrison was also named in the suit for allegedly failing to appropriately supervise the medical staff.
Dr. Harrison ordered the correct medications and therefore the case against her appeared to be defensible. Nonetheless, she was in the case for the long run. There was a clear error on the part of Nurse Weiss. The medication was appropriately labeled. She simply failed to check the medication before administering it to the patient through the IV.
Medical records were obtained, written discovery was exchanged by the parties, experts were consulted, and depositions took place. One aspect of the case that was clear early on, there was not going to be a standard of care defense for the error committed by Nurse Weiss.
Nurse Weiss testified in her deposition that she had never made such a grave error in her career as a nurse. She willfully admitted the mistake. While admitting that she failed to read the label, her testimony revealed that part of the problem was the drugs were stored in the refrigerator and were not properly organized or separated.
As is often the case in medical malpractice litigation, Mr. Gray testified that life was not the same after this incident. His pre-existing conditions were worse due to the profound effects of the medication error. He could no longer get out and ride his motorcycle. He had trouble keeping his house. He required more medical care. His memory was not as good as it was before the medication error.
There is a legal doctrine called the eggshell skull rule, which means the alleged wrongdoer takes the victim as he or she is found. In other words, a defendant medical provider can be held responsible for an exacerbation of pre-existing conditions. This can cause monetary damages to spiral upwards. That was going to be the proof presented to a jury if the case went to trial. There was also going to be some countervailing proof that Mr. Gray was exaggerating his claims. Fortunately, and quite miraculously, he had a good recovery.
Based on the facts and proof that was developed, both parties decided to mediate the case and avoid the risks of a jury trial. It was concerning that Nurse Weiss was not going to have a standard of care defense. Plaintiff’s counsel likely knew that a jury may not find credible some of the claims that Mr. Gray was making about permanent injuries.
Ultimately, the case against Dr. Harrison was defensible. She was dismissed from the case. In this instance, the law was not going to hold her directly or vicariously liable for Nurse Weiss’s acts. The case settled at mediation on behalf of Ms. Weiss and the surgery center.
The Lessons
Does your practice have a medication administration protocol? If so, is it sufficient?
It is imperative that every medical practice has a protocol for storing and administering medicine. Specific precautions should be taken to avoid medication errors.
practice, but taking time to be sure you follow the “Five Rights” can avert serious
harm. In other words, ensure you have the right patient, right drug, right dose, right
route, right time.
[1] Ascension_Saint_Thomas_Hospital_2567_reviewed_8262026_R.pdf
[2] Tariq RA, Vashisht R, Sinha A, et al. Medication Dispensing Errors and Prevention. [Updated 2024 Feb 12]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK519065/
[3]Naseralallah, Lina et al. “Prevalence, contributing factors, and interventions to reduce medication errors in outpatient and ambulatory settings: a systematic review.” International journal of clinical pharmacy vol. 45,6 (2023): 1359-1377. doi:10.1007/s11096-023-01626-5: https://pubmed.ncbi.nlm.nih.gov/37682400/
[4] https://www.svmic.com/articles/373/closed-claim-a-recipe-for-a-medical-emergency
The contents of The Sentinel are intended for educational/informational purposes only and do not constitute legal advice. Policyholders are urged to consult with their personal attorney for legal advice, as specific legal requirements may vary from state to state and/or change over time.
